What Is the meaning of the Anion Gap?
The anion gap is a derived value that assists clinicians interpret acid-base balance by comparing measured serum sodium against measured serum chloride and serum bicarbonate. It is not a directly measured lab result. Instead, it is a helpful diagnostic marker derived from a standard chemistry panel, often supported by an anion gap calculator for quick clinical interpretation.
At a fundamental level, the anion gap reflects the difference between the positively charged ions and the negatively charged ions reported in routine serum electrolytes. Because the body must remain electrically balanced, this gap can reveal hidden acids in the blood when the balance shifts. That is why the anion gap is often part of the evaluation for metabolic acidosis and other acid-base disorder patterns.
The commonly used calculation formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
When the value is elevated, it often signals unmeasured acids in the bloodstream. When it is normal, it does not always mean the patient is stable, but it does narrow the differential diagnosis. In practice, the anion gap is one of the most helpful tools for reviewing laboratory values in the setting of illness, dehydration, or suspected metabolic derangement.
How come anion gap Matters in diabetic ketoacidosis
diabetic ketoacidosis is a well-known cause of high anion gap metabolic acidosis. In diabetic ketoacidosis, the body cannot use glucose effectively because of low insulin, so it begins breaking down fat for fuel. This process produces ketone compounds, including beta-hydroxybutyrate, which collect and drive anion gap increase.
As ketones rise, they increase ketone accumulation and deplete bicarbonate, which contributes to bicarbonate loss and a decreasing serum bicarbonate level. The result is worsening acidemia and a marked disturbance in the acid-base balance. A patient with DKA may also have dehydration, electrolyte imbalance, and worsening acidosis progression, all of which affect the clinical picture.
The anion gap calculation helps separate DKA from other causes of metabolic acidosis. It is especially useful when symptoms are nonspecific or when a blood gas has not yet been obtained. Together with glucose, ketones, and the electrolyte panel, it helps confirm the diagnosis and track how severe the metabolic derangement is.
Because DKA can develop rapidly, an anion gap calculator can be a helpful way to read the chemistry profile in real time. It does not substitute for clinical judgment, but it helps better clinical interpretation when reading serum electrolytes, blood gas results, and ketone testing together.
How to Calculate the Anion Gap
The standard anion gap formula relies on the sodium level, chloride, and bicarbonate values from an electrolytes panel. Most methods omit potassium, although some clinicians factor in it in particular contexts. A common calculation is:
Anion gap = sodium - (chloride + bicarbonate)
For example, if serum sodium is 140, serum chloride is 100, and serum bicarbonate is 12, the anion gap is 28. Such a rise strongly suggests an acid load from unmeasured anions, such as ketones in DKA.
However, the raw number may be misleading when albumin is low. Albumin is a key unmeasured anion, so low albumin can make the anion gap appear falsely normal or only mildly elevated. That is why a corrected anion gap is often used when interpreting metabolic acidosis. This adjustment enhances accuracy, especially in critically ill patients, where protein levels may be altered.
Using an anion gap calculator can streamline the process, especially when it includes albumin correction. A corrected value is often more useful for assessing whether the patient has ongoing acid retention or whether the measured gap is being masked by hypoalbuminemia. This is important in both diagnosis and monitoring trend over time.
In DKA, the calculation should always be interpreted in combination with the blood gas, potassium, glucose, ketones, and the overall clinical picture. The number alone is informative, but the pattern matters more than a single result.
Typical Anion Gap Values in DKA
A normal anion gap generally lies within the laboratory normal range, though exact thresholds vary by method and instrument. Many labs report values near 8 to 12 mEq/L, but the accepted range depends on the local blood chemistry system and the lab’s calibration. As a result, clinicians should always use the reference interval from the reporting laboratory.
In high anion gap metabolic acidosis, the anion gap is increased because unmeasured acids are present in excess. DKA is one of the most recognizable examples. The greater the gap, the more likely there is significant ketone accumulation, though the degree of elevation may not always perfectly match symptom severity.
Blood chemistry in DKA often shows:
- Increased glucose Reduced serum bicarbonate Variable serum chloride Shifts in potassium Raised ketones, especially beta-hydroxybutyrate
It is important to remember that the anion gap is a clue, not a diagnosis by itself. DKA is usually confirmed by the combination of hyperglycemia, ketones, and metabolic acidosis. When read carefully, the anion gap helps support the presence of an acid burden and helps guide the urgency of treatment.
How the Anion Gap Changes During DKA Treatment
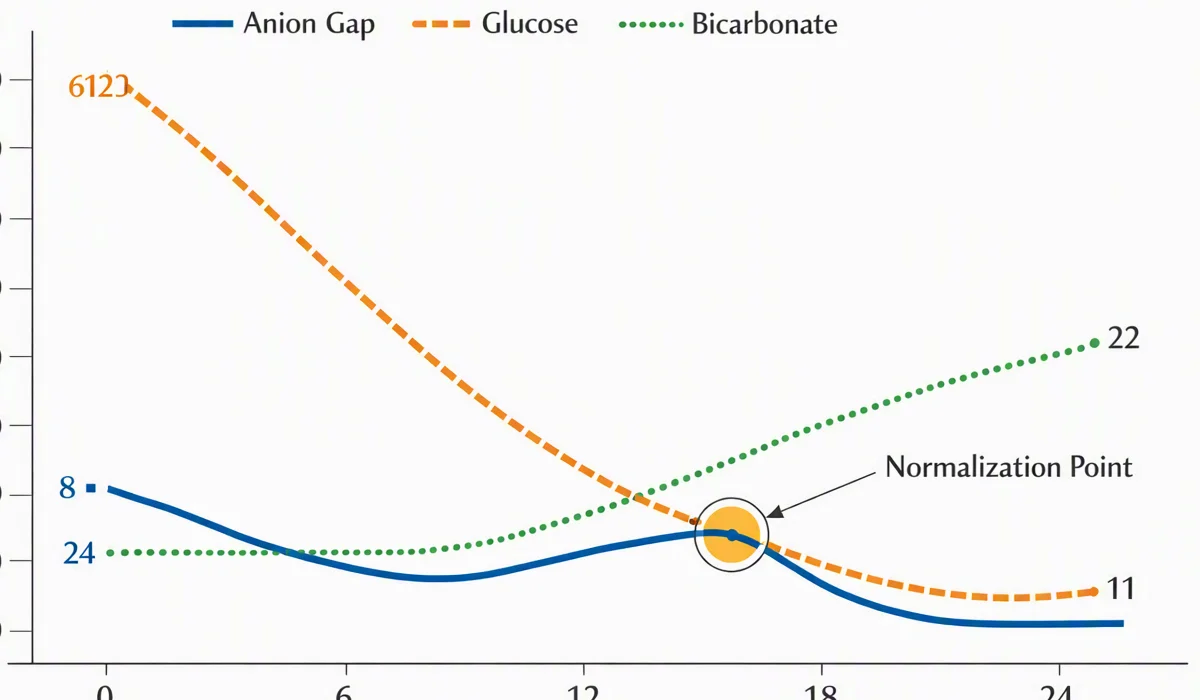
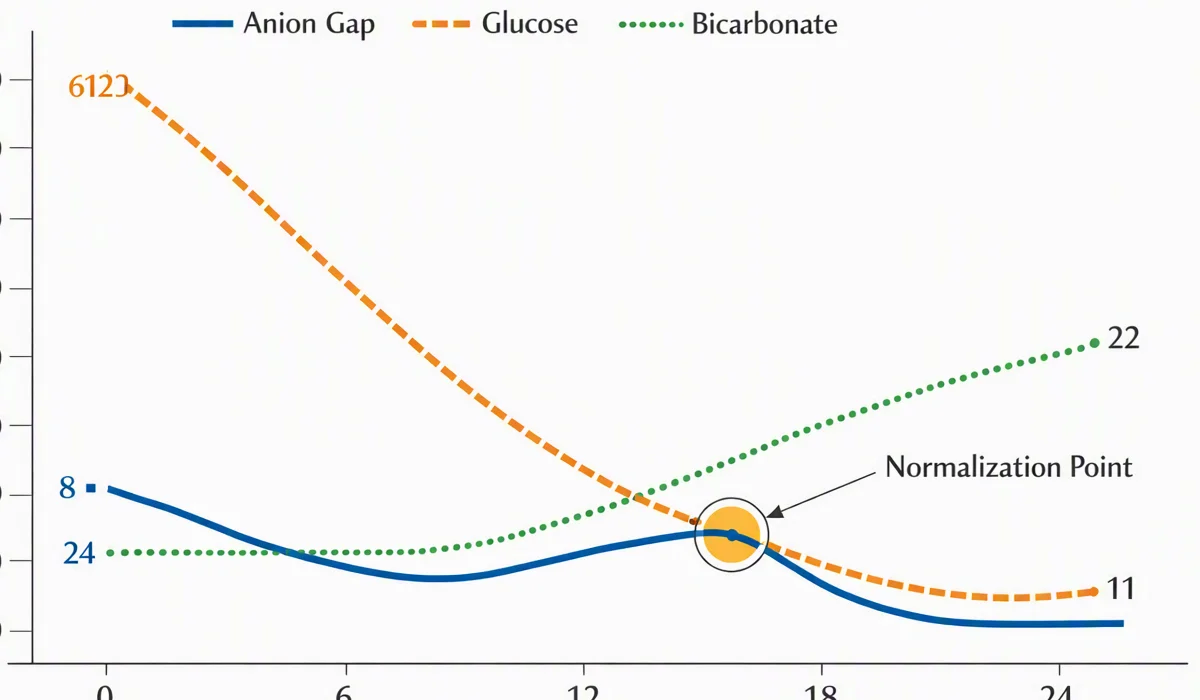
As treatment begins, the anion gap should generally drop if the therapy is effective. This shift reflects ketone clearance, which occurs as insulin therapy stops ongoing ketone production and helps the body process glucose again. Intravenous fluids also improve circulation, decrease dehydration, and support renal clearance of acids and ketones.
During recovery, serum bicarbonate typically rises as acid production falls and buffering gets better. This is often described as bicarbonate recovery. A closing anion gap is one of the clearest signs that the metabolic acidosis from DKA is improving.
That said, the anion gap may not normalize immediately, especially if ketone bodies remain in circulation or if treatment has only partially treated the underlying problem. Monitoring trend is more helpful than relying on a single repeat value. Clinicians often follow the electrolyte panel and blood gas together to assess treatment response.
It is also common for potassium to change during therapy. Even if potassium is normal or high at presentation, it may decline after insulin and fluids begin. This does not directly determine the anion gap, but it is a critical part of the overall acid-base and electrolyte picture.
In short, lowering anion gap values usually indicate that treatment is working. Rising or persistent values suggest ongoing acid generation, incomplete ketone clearance, or another cause of acidosis that deserves review.
The Anion Gap vs. Bicarbonate: What is the Difference?
The anion gap and bicarbonate are connected but not identical. Bicarbonate shows one part of the body’s acid-buffering system, while the anion gap reflects the presence of extra acids. Both are crucial to understanding acid-base status, but they address different questions.
A low bicarbonate level tells you that acidosis is present or that the buffer has been consumed. A raised anion gap tells you that the acidosis is likely caused by unmeasured anions such as ketones, lactate, or toxins. In DKA, both are often abnormal at the same time.
This distinction matters because other acid-base disorders can seem alike at first glance. For example, lactic acidosis can also elevate the anion gap, and a patient may have both DKA and lactic acidosis at the same time. Blood gas results, lactate testing, and the clinical context help determine the cause.
Think of bicarbonate as the “what is low?” number and the anion gap as the “what is accumulating?” number. In tandem they provide a much clearer view of the patient’s metabolic state than either value alone. This is why the anion gap calculator is so helpful in practice: it helps relate the chemistry profile to the underlying physiology.
When a Normal Anion Gap Does Not Exclude DKA
A typical anion gap does not always rule out DKA. This remains one of the biggest pitfalls in clinical interpretation. A patient can have a overlapping acid-base disorder, where one process elevates the https://anion-gap-estimator988.timeforchangecounselling.com/how-to-use-an-anion-gap-calculator-in-iron-poisoning-cases gap while another decreases it. As a result, the final number may appear misleadingly normal.
One common reason is hyperchloremia. During treatment or due to fluid shifts, chloride can rise and offset the unmeasured anions, producing hyperchloremic acidosis. In this setting, ketones may still be present, but the gap no longer appears elevated in the expected way.
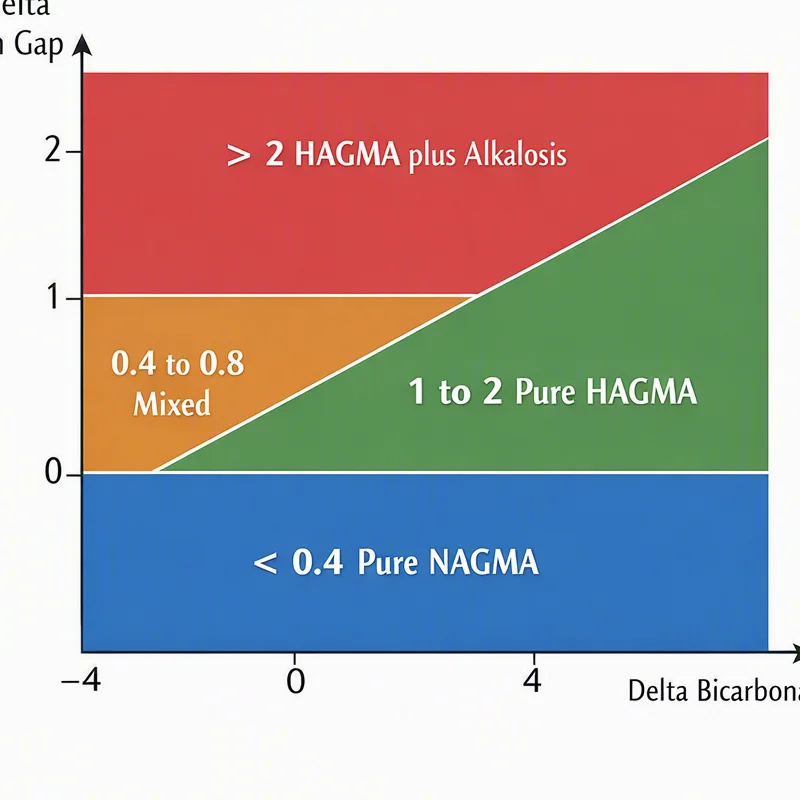
The delta gap can help identify this problem. It measures the change in anion gap to the change in bicarbonate and helps reveal whether more than one acid-base process is occurring. If the relationship does not fit typical DKA, a complex disorder should be considered.
Ongoing ketosis is another clue. A normal gap may coexist with ongoing ketone production, especially if treatment has started but has not fully corrected the underlying insulin deficiency. That is why ketones, blood gas, and electrolyte values all should be considered together. A single normal gap should never stop the evaluation when the clinical picture still suggests DKA.
Frequent Errors In Interpreting the Anion Gap
One common mistake is overlooking albumin correction. Reduced albumin can conceal a true anion gap elevation and lead to underestimation of the severity of metabolic acidosis. This is particularly important in critically ill patients or those with poor nutrition, inflammation, or prolonged illness.
Another mistake is assuming all elevated gaps is DKA. Even though DKA is common, other problems such as lactic acidosis, kidney failure, or toxin exposure can also increase the gap. Thorough clinical assessment is required to identify the true cause of the acid-base disorder.
Lab variation also matters. Different laboratories may use slightly different methods, producing different reference interval cutoffs. For this reason the same patient can appear to have a different gap depending on where the blood chemistry is processed.
A further issue is ignoring broader electrolyte imbalance. Sodium, chloride, bicarbonate, and potassium all affect the interpretation. If one value is shifting because of fluids, renal function, or treatment, the anion gap may change in ways that reflect therapy rather than disease progression.
Ultimately, clinicians sometimes rely too heavily on the number alone. A good diagnostic interpretation requires the anion gap, ketones, glucose, blood gas, lactate, albumin, and the clinical presentation. The anion gap calculator is most useful when it is used as part of that larger assessment rather than as a stand-alone answer.
Frequently Asked Questions About the Anion Gap in DKA
What does an elevated anion gap indicate in diabetic ketoacidosis?
A high anion gap in diabetic ketoacidosis usually means that unmeasured acids, mainly ketone bodies such as beta-hydroxybutyrate, are accumulating in the blood. This pattern supports high anion gap metabolic acidosis and helps confirm the diagnosis when combined with glucose, ketones, and blood gas results.
What is the normal anion gap range?
The normal anion gap range depends on the laboratory reference interval, but many labs report a value roughly around 8 to 12 mEq/L. The exact cutoff can vary because of lab methods, so the reporting lab’s range should always be used when interpreting serum electrolytes.
How do you determine the anion gap with albumin adjustment?
You first calculate the basic anion gap using sodium minus chloride plus bicarbonate. Then you adjust for albumin because low albumin can hide a true elevation. A corrected anion gap gives a more precise estimate of the acid burden when albumin is low, enhancing clinical interpretation.
Can diabetic ketoacidosis happen with a normal anion gap?
Yes. DKA can sometimes appear with a normal anion gap if there is a mixed acid-base disorder, hyperchloremic acidosis, or partially treated ketosis. Persistent ketosis may still be present even when the gap is no longer elevated, so the full electrolyte panel and blood gas should be reviewed.
How does the anion gap change after DKA treatment starts?
As insulin therapy and intravenous fluids begin taking effect, the anion gap usually drops because ketone clearance improves and bicarbonate recovery begins. A falling gap is a useful sign of treatment response, but the trend should be interpreted alongside potassium, ketones, and other laboratory values.