An anion gap calculator is more informative than a simple calculator when you need rapid, precise diagnostic interpretation of serum electrolytes. In practice, the anion gap helps clinicians evaluate acid-base balance, screen for metabolic acidosis, and narrow a broad differential diagnosis by identifying likely causes of unmeasured anions from disorders driven by clear bicarbonate loss or chloride retention. If used correctly, it becomes part of a broader diagnostic algorithm rather than a stand-alone value.
This guide covers how the anion gap formula works, how to interpret a normal anion gap versus an elevated anion gap, and how to adjust for hypoalbuminemia using albumin correction. It also illustrates how to connect the result to real-world causes such as lactic acidosis, ketoacidosis, renal failure, renal tubular acidosis, and toxic alcohol ingestion.
How the Anion Gap Measures
The anion gap is a computed value derived from common electrolytes on a basic metabolic panel. It estimates the difference between measured positively charged ions and measured negatively charged ions, helping clinicians detect the presence of unmeasured anions in the blood. Since the body maintains tight acid-base balance through buffer systems and kidney function, changes in the gap can suggest a meaningful metabolic derangement.
In the classic interpretation, sodium is compared against chloride and bicarbonate, which are the main contributors in routine chemistry testing. The gap represents the balance between these measured ions and other charged particles not directly reported, such as proteins, phosphate, sulfate, lactate, and organic acids. This is why the gap can uncover a hidden acid-base disorder even before the precise cause is known.
The test is often used as part of clinical assessment when a patient presents with low bicarbonate, altered mental status, unexplained tachypnea, or an abnormal metabolic profile. A single number does not make the diagnosis, but it can quickly steer attention toward the right branch of the differential diagnosis.
Anion Gap Calculation and Calculation Inputs
The basic anion gap equation is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Certain clinicians include potassium in the equation, particularly in older references or specific methods:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
Most modern clinical use focuses on the sodium-based version because potassium is usually low in relation to sodium and offers minimal benefit to routine interpretation. Even so, an anion gap calculator may support either approach, so it is important to know which formula is being applied. Minor variations in the equation can shift the number enough to affect clinical decision-making.
The main inputs are drawn from the electrolyte panel or chemistry panel: sodium, chloride, and bicarbonate. In many cases, the calculator also asks for albumin because low protein levels can mask a clinically important elevation. Since serum albumin level strongly influences the baseline gap, a raw number without context can be misleading.
As an example, a patient with sodium 140, chloride 104, and bicarbonate 24 has an anion gap of 12. That value may be normal depending on the lab’s reference range, but the interpretation changes if the patient has severe hypoalbuminemia or evidence of metabolic acidosis. The calculation is only the starting point for diagnostic interpretation.
How to Understand a Typical vs Increased Anion Gap
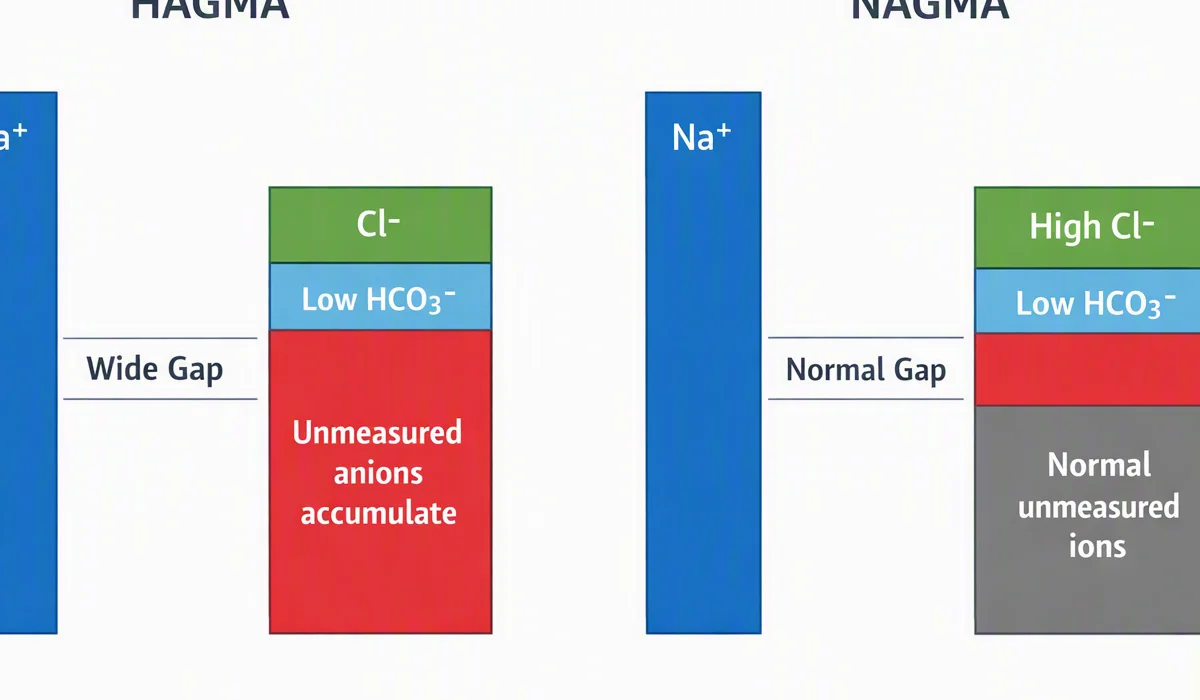
Assessment starts with the lab’s reference range, since standard results vary slightly by assay and institution. In general, a normal anion gap suggests that the bicarbonate decrease is being counteracted by a rise in chloride, while an elevated anion gap implies accumulation of unmeasured acids or their anions. Both patterns can indicate metabolic acidosis, but they suggest different etiologies.
A high anion gap metabolic acidosis usually means acid is being added to the body or retained because the kidneys cannot clear it effectively. Common causes include organic acids and toxins. By contrast, a normal anion gap metabolic acidosis is often a hyperchloremic process, where bicarbonate is lost and chloride rises to maintain electroneutrality.
Practical interpretation works best as a branching diagnostic algorithm:
- Normal anion gap: think bicarbonate loss or renal acid-handling problems. Elevated anion gap: think added acids, accumulation of acids, or toxin exposure. If the number seems unexpectedly normal, check albumin and consider anion gap correction.
It is equally important to confirm whether the patient really has metabolic acidosis. Low bicarbonate levels on a chemistry panel is not enough by itself; an arterial blood gas can help clarify pH and respiratory compensation. This is especially valuable when mixed acid-base disorders are possible.
Revised Anion Gap for Low Albumin
Albumin is a key not directly measured anion, so reduced albumin decreases the observed anion gap. That means a patient with hypoalbuminemia may have a misleadingly unchanged or only mildly elevated result despite important acidosis. This is why albumin correction matters in everyday interpretation.
The corrected anion gap raises the measured value upward when serum albumin is below normal. Several correction methods have been described, but a common clinical approach is to add a fixed amount for each gram per deciliter albumin is below normal. The exact factor may differ by institution, so the calculator should be used in line with local practice or its stated assumptions.
This anion gap correction is especially important in severely ill patients, patients with malnutrition, liver disease, chronic inflammation, or nephrotic states. In these settings, the raw number may miss the burden of unmeasured anions and therefore hide a true acid-base disorder.
Consider this clinical logic: a patient https://anion-gap-values214.wordcanopy.com/posts/does-lactic-acidosis-increase-the-anion-gap has low bicarbonate and a “normal” gap, but the serum albumin level is markedly reduced. After albumin correction, the gap becomes elevated, revealing a mixed picture or a hidden high-gap process. In other words, the corrected number can alter the differential diagnosis and the urgency of workup.
Clinical Differential of high anion gap metabolic acidosis
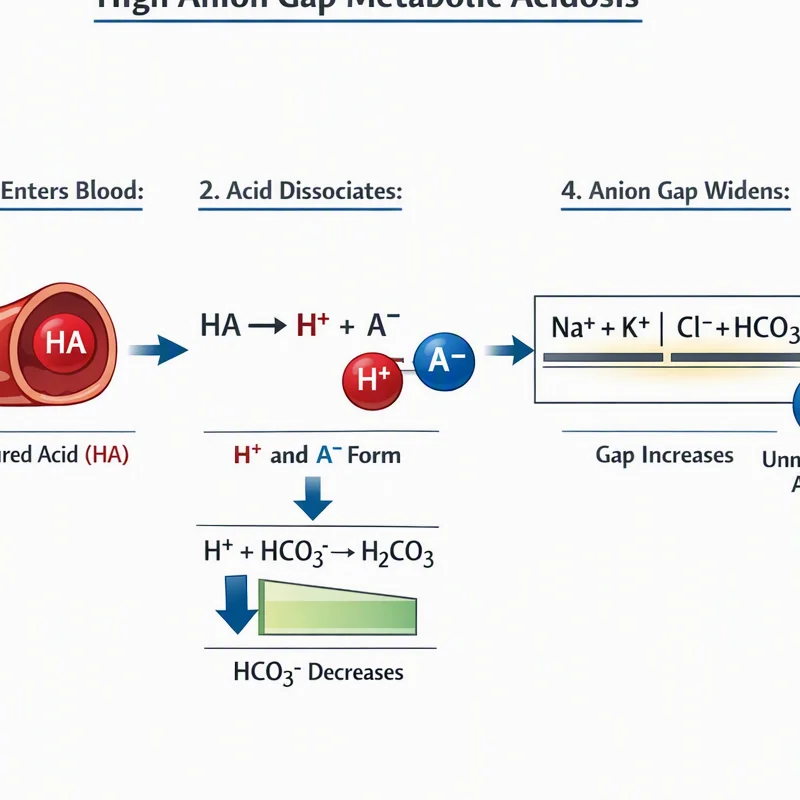
high anion-gap metabolic acidosis develops when acids accumulate or are retained. The main point is that bicarbonate is consumed while the associated anions are not measured in the standard panel. The outcome is a expanded gap and a focused differential.
Frequent causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. Each one has typical clinical clues, but similarity is common, so the anion gap should be interpreted together with history, exam, and lab values.
- Lactic acidosis: commonly caused by hypoperfusion, sepsis, hypoxemia, or severe metabolic stress. Ketoacidosis: encompasses starvation ketosis, alcoholic ketosis, and diabetic ketoacidosis, which commonly presents with hyperglycemia, dehydration, and ketones. Renal failure: impaired acid excretion leads to build-up of acids and gradual metabolic derangement. Toxic alcohol ingestion: like methanol or ethylene glycol, which can lead to severe high-gap acidosis and end-organ injury.
In diabetic ketoacidosis, the gap is often markedly increased because ketone bodies pile up. Within kidney failure, the pattern may evolve with increasing retained acids and a reduction in renal filtration. With toxic alcohol intake, the anion gap can rise early, and the clinical picture may include osmolar gap alterations, visual symptoms, neurologic deterioration, or kidney injury depending on the agent.
By using an anion gap calculator in this setting helps guide the next action in clinical assessment: measuring lactate, ketone assessment, toxicology review, or renal assessment. The number cannot replace judgment, but it sharpens the differential diagnosis.
Differential Diagnosis of normal anion gap metabolic acidosis
A normal anion gap metabolic acidosis is often called hyperchloremic acidosis because chloride rises as bicarbonate falls. In this case, the issue is usually not the addition of unmeasured acid, but rather loss of bicarbonate or impaired renal acid handling. The anion gap remains normal because chloride substitutes for the lost bicarbonate.
Common causes include diarrhea and renal tubular acidosis. Gastrointestinal bicarbonate loss is a classic mechanism in diarrhea, especially when losses are prolonged or severe. The kidneys may also fail to acidify urine properly in renal tubular acidosis, producing a chronic or recurrent normal-gap acidosis.
Other contributors to normal anion gap metabolic acidosis can include high-volume saline administration, certain medications, and tubular dysfunction, but the main clinical distinction remains the same: chloride increases as bicarbonate falls. This is why the serum chemistry pattern matters as much as the calculated number.
When evaluating a normal-gap pattern, ask whether the problem is a true loss of alkali. If the answer is yes, then loss of bicarbonate from the gut or kidney becomes central to the diagnostic workup. That makes the anion gap an efficient tool for directing the next branch of the acid-base differential diagnosis.
Typical Assessment Issues and Medical Setting
Even a accurate calculation can be misleading if the clinical situation is ignored. One common issue is lab error, such as sample contamination, transcription error, or a inconsistent set of results. Before assuming that a major acid-base problem is occurring, confirm that the lab values are coherent and aligned with the patient’s condition.
A further mistake is missing albumin. If the protein concentration is reduced, the raw anion gap may miss the true burden of unmeasured anions. For this reason albumin correction should be taken into account in any patient with suspected metabolic acidosis and low albumin.
The delta gap is another important concept. When the anion gap is raised, the delta gap compares the rise in the gap to the fall in bicarbonate. This helps detect mixed acid-base disorders, such as coexisting metabolic alkalosis or an additional normal-gap acidosis. In practice, the delta gap can indicate whether the patient’s metabolic profile is more intricate than the first calculation suggests.
Other common pitfalls include using the improper reference range, failing to verify pH on an arterial blood gas, and interpreting a single number without considering respiratory compensation. The best results come from combining the calculator output with a full clinical assessment and the broader picture of electrolyte imbalance and organ function.
When It Is Appropriate to Use an Anion Gap Calculator in Medical Workflow
An anion gap calculator is most helpful early in the evaluation of suspected acid-base disorder. It fits naturally into a workflow that begins with a basic metabolic panel or electrolyte panel, then progresses to an arterial blood gas when pH and compensation need clarification. This sequence promotes efficient clinical decision support and more focused testing.
Use the calculator if bicarbonate is decreased, when unexplained tachypnea is present or altered mental status, or when toxin exposure is suspected, sepsis, renal dysfunction, or ketoacidosis. It is also useful during serial lab review because changes in the anion gap can reflect improvement or progression in the underlying metabolic derangement.
In practical terms, the workflow often looks like this:
- Check the basic metabolic panel for sodium, chloride, and bicarbonate. Perform the anion gap calculation using the calculator. Check albumin and apply corrected anion gap logic if needed. Obtain an arterial blood gas to confirm acidemia or alkalemia and assess compensation. Move to the appropriate differential diagnosis for high-gap or normal-gap causes.
This approach makes the calculator part of a broader clinical decision-making process rather than a standalone number generator. It helps clinicians move quickly from a chemistry abnormality to a meaningful explanation, especially in time-sensitive settings.
FAQ About Anion Gap Interpretation
What is an anion gap calculator used for?
An anion gap calculator is used to calculate the difference between measured cations and anions on a chemistry panel. Clinically, it helps identify metabolic acidosis, support acid-base differential diagnosis, and differentiate between high-gap and normal-gap causes of acid-base disorders. It is especially helpful when combined with albumin and arterial blood gas data.
How do you calculate the anion gap?
The most common anion gap formula is sodium minus the sum of chloride and bicarbonate: sodium − (chloride + bicarbonate). Some methods also add potassium, but the sodium-based formula is most commonly used. The values usually come from a basic metabolic panel or related electrolyte panel.
Why does low albumin affect the anion gap?
Albumin is a primary unmeasured anion, so when hypoalbuminemia is present, the measured gap can look lower than it truly is. That is why albumin correction is important. A corrected anion gap more accurately reflects the real burden of unmeasured acids and improves diagnostic interpretation.
What causes a high anion gap metabolic acidosis?
Common causes of high anion gap metabolic acidosis include lactic acidosis, ketoacidosis, diabetic ketoacidosis, renal failure, and toxic alcohol ingestion. These conditions increase unmeasured acids or impair acid clearance, increasing the gap and signaling a significant metabolic problem.
Can a normal anion gap still occur with metabolic acidosis?
Yes. A patient can have normal anion gap metabolic acidosis, also called hyperchloremic acidosis. This pattern often occurs with diarrhea or renal tubular acidosis, where bicarbonate loss is balanced by a rise in chloride. In that setting, the gap stays normal even though true acidosis is present.