Understanding an Anion Gap?
The anion gap is a derived value that helps to evaluate acid-base balance and recognize trends in a patient’s electrolytes. It compares https://anion-gap-app417.hexaforgey.com/posts/the-importance-of-albumin-correction-can-affect-results-in-anion-gap-interpretation measured positive and negative ions in a typical electrolyte panel, usually using serum sodium, serum chloride, and serum bicarbonate. Because not every ion is directly checked on routine serum chemistry testing, the anion gap acts as a useful helpful guide when reviewing a lab result.
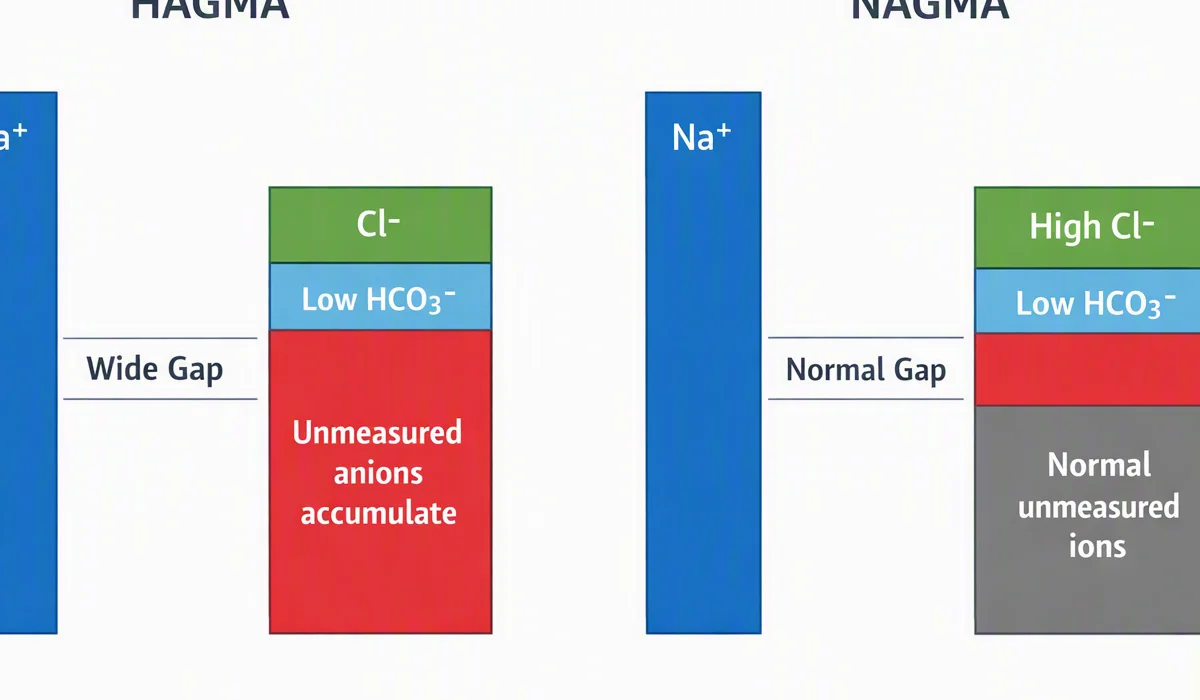
In practical terms, the anion gap helps clinicians think through an acid-base disorder by showing whether there are unmeasured anions contributing to metabolic acidosis. A above-normal value can point toward conditions with excess acids, while a normal value can suggest that bicarbonate has been lost and replaced by chloride. That distinction is especially important when evaluating normal anion gap acidosis, also called non-anion gap metabolic acidosis or hyperchloremic metabolic acidosis.
The concept is basic, but the interpretation can be complex. Because sodium is a major measured cation and chloride and bicarbonate are major measured anions, the balance among them reflects the body’s internal chemistry. When serum chloride rises as bicarbonate falls, the anion gap may remain unchanged even though acidosis is present. That is why the anion gap is not just a number; it is part of a broader clinical analysis of a patient’s metabolic state.
How an Anion Gap Calculator Works
An anion gap calculator simplifies the calculation formula and reduces the chance of arithmetic errors. In its most basic form, the formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
This calculation uses routine laboratory values from an electrolyte panel. Some calculators may also use an albumin correction, because serum albumin is a major unmeasured anion and can change the expected value. When albumin is low, the raw anion gap may seem lower than it truly is, which can mask clinically important findings.
The calculator is most helpful when a clinician wants a rapid interpretation guide for a patient with suspected acidosis. It gives a quick estimate of whether the result falls within the expected reference interval or indicates a deviation that needs more evaluation. A normal lab result does not always mean there is no problem; it may simply mean that the pattern is consistent with bicarbonate loss rather than added acids.
Many calculators also help identify a corrected anion gap by modifying for hypoalbuminemia. That correction can be important in ill patients, where low albumin is common and may alter the apparent picture. In other words, the calculator is a handy shortcut, but its output still requires careful clinical interpretation in light of the full clinical context.
Standard Anion Gap Acidosis Overview
Normal anion gap acidosis is an example of metabolic acidemia in which the measured anion gap remains within the usual range despite a decrease in bicarbonate. It is also called non-anion gap metabolic acidosis and hyperchloremic acidosis because chloride often rises to compensate for the lost bicarbonate. This keeps the anion gap from increasing even though the body’s acid-base equilibrium has shifted toward an acidic state.
This pattern is unlike high anion gap acidosis, where unmeasured acids accumulate. In normal anion gap acidosis, the key issue is usually bicarbonate depletion or impaired renal acid handling rather than the accumulation of new acids. The result is often described as a mild acidosis, but the severity depends on the underlying cause and the patient’s overall health.
Recognizing this pattern is important because it narrows the differential diagnosis. A calculator can reveal that the anion gap is not elevated, but that finding should prompt attention to chloride, bicarbonate, and the likely source of bicarbonate loss. In that sense, the anion gap calculator is a first step for evaluation, not the final answer.
Common Causes of Regular Anion Gap Acidosis
Several states can lead to normal anion gap acidosis. A common cause is diarrhea, which causes gastrointestinal bicarbonate loss. When bicarbonate is lost from the gut, the body may retain chloride to maintain electrical neutrality, producing a high chloride picture and a normal anion gap.
An additional important cause is renal tubular acidosis, a group of disorders in which the kidneys have trouble with kidney acid handling. In these conditions, the kidneys fail to excrete acid properly or fail to reclaim bicarbonate efficiently. The result can be a ongoing non-anion gap metabolic acidosis even when kidney function is otherwise not markedly reduced.
Chloride-rich intravenous fluids can also contribute. Substantial amounts of chloride-rich solutions may dilute bicarbonate and increase serum chloride, leading to hyperchloremic metabolic acidosis. This is especially useful when reviewing recent treatments, because the acid-base pattern may reflect therapy rather than a primary disease process.
Other possible causes include certain medications, fistulas, or renal disorders, but the most useful broad categories are diarrhea, renal tubular acidosis, and chloride load. When the underlying cause is not obvious, the anion gap calculator can help direct the workup on these pathways.
How to Interpret the Result
Assessing the result starts by checking the serum electrolytes together, not in isolation. A low bicarbonate level plus a normal anion gap and elevated chloride often indicates hyperchloremic metabolic acidosis. The next question is whether the pattern fits GI loss, renal loss, or another source of bicarbonate loss.
Potassium is also important. Some forms of renal tubular acidosis are associated with low potassium, while others may present with high potassium. That detail can help narrow the differential diagnosis and suggest which kidney acid handling defect is most likely.
The clinical context matters just as much as the numbers. A lab pattern consistent with metabolic acidosis may be observed in a patient with diarrhea, recent fluid administration, or kidney disease. The calculator should therefore be used alongside a broader assessment that includes symptoms, medications, volume status, and recent treatments.
In practice, the best approach is to combine the calculator output with a careful clinical interpretation of the serum bicarbonate level, chloride level, potassium level, and the patient’s overall presentation. This helps determine whether the result reflects a transient change or a more significant acid-base disorder.
When to Adjust the Anion Gap for Albumin
Albumin is one of the key unmeasured anions in plasma, so low serum albumin can lower the observed anion gap. This means that a patient with hypoalbuminemia may have a deceptively normal or low anion gap even when another process is present. In those cases, using a corrected anion gap gives a more accurate assessment.
Albumin correction is especially helpful when the clinical picture suggests more than simple bicarbonate loss. If the uncorrected value looks normal but the patient appears significantly ill, the correction may reveal a hidden disturbance. This is a matter of protein binding and electrical balance, not just arithmetic.
Many anion gap calculators include albumin adjustment because it enhances interpretation in patients with low protein levels. The key point is that the raw number can be deceptive when albumin is low. If a clinician ignores this, a mixed acid-base disorder may be missed.
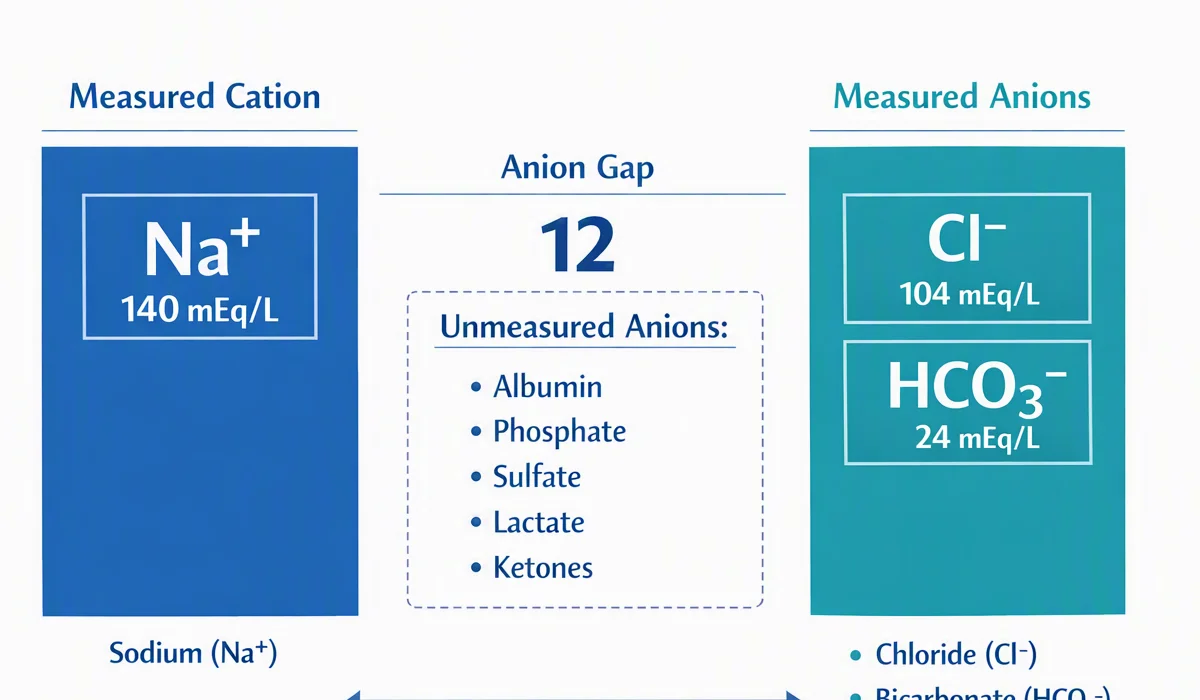
As a rule, the lower the albumin, the more thorough the interpretation should be. Albumin correction does not take the place of clinical judgment, but it can improve the accuracy of the anion gap as a screening tool and help uncover an otherwise obscured acid-base disorder.
Stepwise Example Calculation
Here is a stepwise example based on standard laboratory values:
Sodium: 140 mEq/L
Applying the formula for calculation:
Anion gap = 140 - (112 + 20)
This gives 140 - 132 = 8 mEq/L.
When the lab’s normal interval for this value is about 8 to 12 mEq/L, this result is within the expected range. Yet the low bicarbonate continues to indicate acid-base acidosis. Because the anion gap is normal, the pattern suggests normal anion gap metabolic acidosis, often related to diarrhea, renal tubular acidosis, or chloride load.
When the patient’s albumin is low, such as with hypoalbuminemia, the adjusted anion gap may be higher than 8. For that reason the calculator should be viewed as part of the diagnostic workflow, not a standalone verdict. A normal raw value can still coexist with another acid-base issue if albumin is reduced or if there is a mixed disorder.
This demonstrates how a calculator supports the overall evaluation. It helps confirm that the pattern is consistent with normal anion gap acidosis and directs attention toward the cause of bicarbonate loss rather than excess unmeasured acids.
When to Order Additional Testing
Further evaluation is needed when the cause is unclear, the patient is symptomatic, or the result does not fit the rest of the clinical picture. A blood gas study can confirm the degree of acidemia and help distinguish respiratory from metabolic contributions. It can be particularly useful if the serum bicarbonate is low but the overall picture is uncertain.
A urine AG may be ordered when renal tubular acidosis is suspected. This may help distinguish kidney acid-handling problems from gastrointestinal bicarbonate loss by estimating whether the kidneys are appropriately excreting ammonium. In the setting of persistent non-anion gap metabolic acidosis, it can be a valuable next step.
Lactate testing may be useful if there is concern for a mixed disorder or if the clinical situation could involve tissue hypoperfusion or a different high-gap process. Even though the anion gap calculator suggests a normal result, lactate can help eliminate additional contributors.
Kidney function tests are also important, especially when renal tubular acidosis, chronic kidney disease, or medication effects are part of the differential diagnosis. In combination with blood gas analysis and urine studies, they help round out the evaluation and determine the underlying cause.

Frequently Asked Questions
What is the normal anion gap range?
The anion gap normal range depends on the laboratory and whether potassium is included in the calculation. Many reference intervals fall around 8 to 12 mEq/L, but the exact range can change by method and analyzer. Always interpret the value using the lab’s own reference interval.
How do you calculate the anion gap with sodium, chloride, and bicarbonate?
Use the calculation formula: serum sodium minus the sum of serum chloride and serum bicarbonate. In other words, anion gap = sodium - (chloride + bicarbonate). An anion gap calculator simplifies this process and helps minimize errors.
Why do you correct the anion gap for albumin?
You correct for albumin because low serum albumin can reduce the measured gap and hide a clinically important disturbance. With hypoalbuminemia, the corrected anion gap gives a more accurate reflection of the true acid-base state.
What causes normal anion gap acidosis?
Common metabolic acidosis causes with a normal gap include diarrhea, renal tubular acidosis, gastrointestinal bicarbonate loss, and exposure to chloride-rich intravenous fluids. These conditions usually lower bicarbonate while increasing chloride, producing hyperchloremic metabolic acidosis.
When should a urine anion gap be performed?
A urine anion gap is frequently used when the reason of normal anion gap acidosis is not clear and renal tubular acidosis is being suspected. It can help separate kidney acid-handling problems from gastrointestinal bicarbonate loss and is best used alongside blood gas analysis, serum electrolytes, and kidney function tests.