An anion gap calculator is a useful diagnostic tool for measuring an acid-base disorder in young patients. It assists clinicians interpret an electrolyte imbalance, determine the likely cause of metabolic acidosis, and determine what additional testing may be needed. As pediatric patients have different physiology, growth patterns, and common illness patterns than adults, the clinical interpretation of the anion gap requires special attention to age, albumin, and the overall picture of lab values and symptoms.
If applied appropriately, this simple calculation can reveal clues about unmeasured anions in the blood and support a broader metabolic evaluation. It is not a stand-alone diagnosis. Rather, it is part of a larger review of serum chemistry, the child’s condition, and any signs of an acidic state that may need urgent care.
How the Anion Gap Evaluates in Children
The anion gap is a computed value that estimates the gap between measured positively charged and negatively charged particles in the blood. Practically speaking, it is derived from serum sodium, serum chloride, and serum bicarbonate. This calculation formula is a way to detect an anion difference that may reflect extra acids or other unmeasured anions.
In children, the anion gap is especially helpful when evaluating metabolic acidosis. If the gap is elevated, it https://anion-gap-reference490.inkharbory.com/posts/can-young-patients-exhibit-different-anion-gap-ranges often suggests the body has accumulated acids that are not directly measured on a basic electrolyte panel. If the gap is normal, the problem may be related to loss of bicarbonate or another process that does not increase unmeasured acids.
Knowing the buffer system matters here. The body maintains pH through coordinated changes in respiration, kidney function, and bicarbonate balance. When that system is disrupted, the anion gap can provide useful interpretive guidance about the direction of the problem. Still, the number itself must be viewed in context with the child’s symptoms, hydration status, and other blood chemistry findings.
Using an Anion Gap Calculator
An anion gap calculator usually takes three inputs: sodium value, serum chloride, and bicarbonate input. They are taken from a standard electrolyte panel or broader serum chemistry testing. The calculator then applies the standard formula to calculate the anion gap.
The usual formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Some laboratories use alternative formulas that account for potassium, but the sodium-based formula is commonly used for pediatric assessment because it is straightforward and consistent. The result should then be compared with the lab’s reference interval and the child’s clinical status.
To use the calculator effectively:
- Provide the most recent blood chemistry values from the same sample when possible. Look for obvious data entry errors before relying on the result. Review whether the child has signs of dehydration, infection, or another condition that changes acid-base balance. Interpret the number alongside the bicarbonate level, not in isolation.
The calculator is best thought of as a quick screen for an acid-base disorder. It does not replace clinical reasoning or a full differential diagnosis. In pediatric care, the real value is in relating the calculation to the child’s symptoms, exam findings, and other lab values.
Children's Normal Ranges and Normal Values
A child reference range for the anion gap may vary a little by laboratory, age range, and test methodology. A normal anion gap does not mean the child is free of illness, and an unexpected result does not always mean illness. It simply provides a clue that must be interpreted carefully.
Young patients may have age-related differences in serum chemistry because the kidneys' function, total body water, diet, and illness patterns shift during development. Newborns, children, and adolescents may all show slightly different patterns in electrolytes and acid-base balance. For this reason, local reference values are important.
Method variation also matters. Different analyzers and measurement methods can change the reported result. A number that appears mildly elevated in one lab may be considered acceptable in another. That is why pediatric interpretation should always use the laboratory reference interval and not rely on a single universal cutoff.
In general, the anion gap is used as a screening marker rather than a final diagnosis. A mildly different value may reflect normal biologic variation, while a larger abnormality suggests a more serious acid-base problem that deserves follow-up.
Adjusting the Anion Gap for Serum Albumin
Serum albumin acts as a key unmeasured anion in blood. If albumin levels are low, the measured anion gap may appear falsely normal or only mildly elevated even when an acid load is present. This is why albumin correction is so important in pediatric care.
Hypoalbuminemia can occur with illness, inflammation, poor nutrition, kidney disease, or fluid shifts. When this happens, the uncorrected number may underestimate the severity of the problem. Calculating a corrected anion gap provides a better estimate of the true acid burden and improves the accuracy of the clinical interpretation.
Although formulas differ, the principle is consistent: if albumin is low, the gap should be adjusted upward to account for the missing negative charge. This is frequently termed the albumin-adjusted gap. The correction is especially important when evaluating a child with a suspected acid-base disorder but a less dramatic anion gap than expected.
Using the corrected result supports better diagnostic reasoning. It can help distinguish a truly normal gap from one that only appears normal because of low albumin. In a child with metabolic acidosis, that distinction can change the differential diagnosis and the next steps in care.
Elevated metabolic acidosis with a high anion gap in Pediatrics
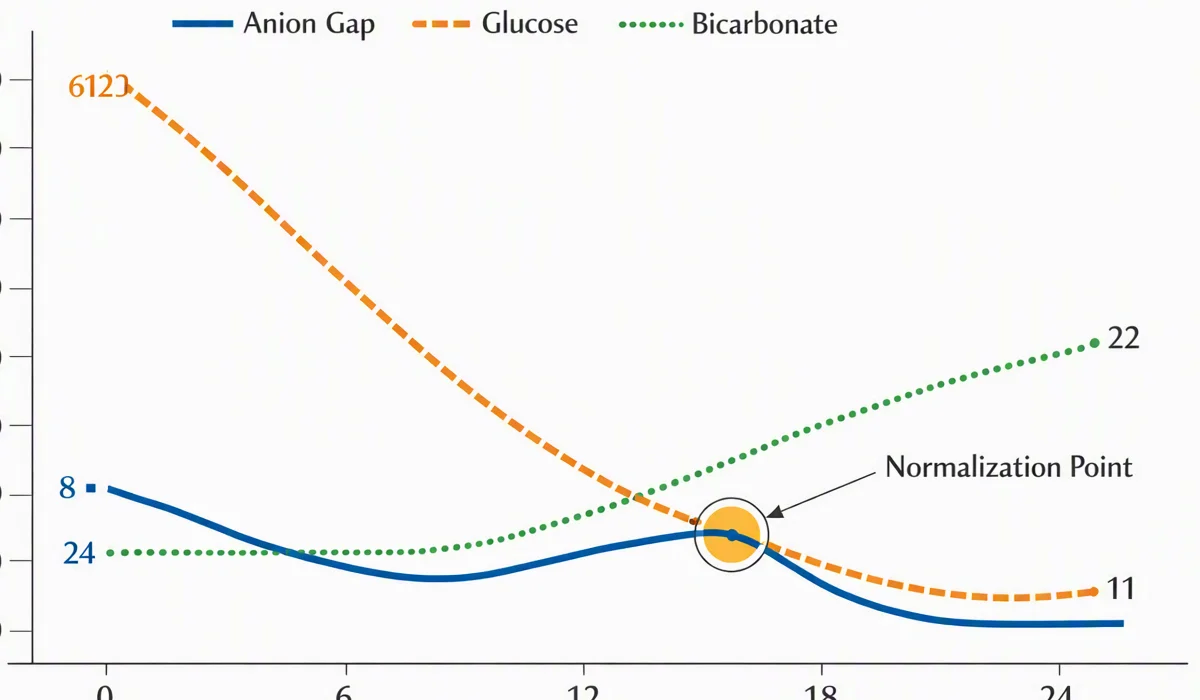
High anion gap metabolic acidosis refers to the fact there is a buildup of acidic compounds or substances that form acid that are not directly measured in the standard electrolyte panel. This is a major reason clinicians use the anion gap calculator in pediatrics. It helps narrow the differential diagnosis and can reveal potentially urgent conditions.
Common causes in children include lactic acidosis, ketoacidosis, and renal failure. These conditions add to unmeasured acids in the blood, lowering bicarbonate and widening the gap. In children, lactic acidosis may occur with poor perfusion, major infection, or shock. Ketoacidosis can occur with diabetes, prolonged fasting, or other states of inadequate carbohydrate use. Renal failure reduces the body’s ability to excrete acid, causing accumulation.
Additional less common causes also belong in the differential diagnosis, especially if the presentation is severe or unexpected. A child with an elevated gap may need urgent evaluation for toxin exposure, tissue hypoxia, or inherited metabolic disorders depending on the history and exam.
When the gap is high, the next question is not just “How high is it?” but “Why is it high?” Such a question guides further testing, treatment priorities, and the level of monitoring needed.
Typical Anion Gap Metabolic Acidosis in Pediatrics
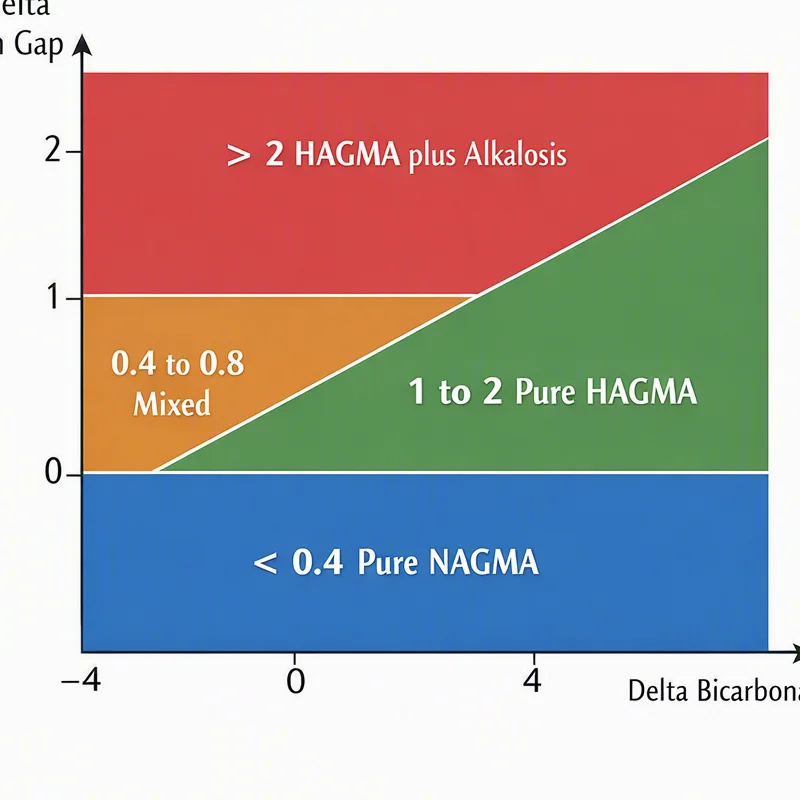
Normal-gap metabolic acidosis is sometimes called hyperchloremic acidosis because chloride often rises as bicarbonate declines. The anion gap remains in the expected limit, but the child still has acid-base acidosis. That is why a normal result should not be dismissed if the clinical picture suggests an acid-base problem.
Two frequent pediatric causes are loose stools and tubular kidney acidosis. With diarrhea, the body loses bicarbonate through the gastrointestinal tract, leading to base loss. In renal tubular acidosis, the kidneys fail to appropriately reclaim bicarbonate or excrete acid, so acid builds up without a large increase in unmeasured anions.
Because the anion gap stays normal, recognition depends on combining the calculation with the bicarbonate level and the overall clinical picture. A child with ongoing diarrhea, reduced intake, or growth concerns may have a normal-gap acidosis that is simple to overlook without careful review of the electrolyte panel.
This is where pediatric assessment matters. A normal gap is not reassuring if the child appears ill, dehydrated, or acidotic. It simply points clinicians toward a different mechanism of acid-base disruption.
Typical Causes, Key Signs, and Subsequent Actions
Several common pediatric illnesses can affect the anion gap and should be considered during interpretation. Harmful swallowing is one important cause of high-gap acidosis, especially when the history is unclear or the child has sudden neurologic changes. Sepsis can cause lactic acidosis through poor tissue perfusion and systemic inflammation. Dehydration may alter labs and worsen acid-base imbalance, especially when accompanied by vomiting, diarrhea, or poor intake.
An arterial blood gas can be very helpful when the electrolyte panel suggests a problem but the severity is uncertain. It provides a direct look at pH, carbon dioxide, and bicarbonate status, helping confirm whether the child truly has metabolic acidosis and whether respiratory compensation is present.
Subsequent steps depend on the clinical setting. In a stable child, repeat testing and careful history may be enough. In a child who appears toxic, lethargic, or severely dehydrated, urgent evaluation is needed. Additional studies may include glucose, lactate, ketones, kidney function tests, toxicology testing, and infection workup. The anion gap is best used as part of a broader metabolic evaluation rather than as a stand-alone answer.
Limitations of Anion Gap Calculation in Children
Although useful, the anion gap has important limitations in pediatric interpretation. One major issue is multiple acid-base abnormalities. A child may have more than one process at the same time, such as vomiting plus sepsis, which can make the gap harder to interpret. In such cases, a “normal” value may hide a significant disturbance, or a high value may reflect combined processes rather than a single cause.
Lab error is another concern. Pre-analytic issues, sample handling problems, or transcription mistakes can distort serum sodium, serum chloride, or serum bicarbonate values. Even small errors can shift the calculated result enough to mislead clinical reasoning.
The albumin effect is especially important in children with illness, immune response, or inadequate intake. If serum albumin is low, the raw number may downplay the true acid burden. That is why a revised result can be more useful than the raw value alone.
Finally, pediatric interpretation requires clinical context. Developmental stage, illness severity, hydration, kidney function, and medication exposure all affect blood chemistry. A value should never be interpreted in isolation from the child’s symptoms, exam, and additional testing.
Used wisely, the anion gap calculator strengthens strong diagnostic reasoning. Used alone, it can confuse. The best approach is to consider the calculation as one part of a well-integrated clinical picture.
Frequently Asked Questions
What is the normal anion gap in pediatric patients?
The pediatric reference range for the anion gap depends on the laboratory method and the child’s age, so there is no universal value. In general, clinicians compare the result with the lab’s stated normal range and consider whether serum albumin is low, because hypoalbuminemia can make the gap look lower than expected.
How do you calculate the anion gap in children?
The standard anion gap calculation uses serum sodium minus the sum of serum chloride and serum bicarbonate. This calculation formula is commonly built into an anion gap calculator and is usually applied to values from the same electrolyte panel for reliable clinical interpretation.
Why should albumin be considered when interpreting the anion gap?
Serum albumin is a major unmeasured anion, so low albumin can mask an elevation in the gap. Using an albumin correction helps estimate the corrected anion gap and reduces the risk of missing an acid-base disorder in a child with hypoalbuminemia.
What leads to a high anion gap metabolic acidosis in pediatrics?
Frequent reasons of high anion gap metabolic acidosis in children include lactic acidosis, ketoacidosis, and renal failure. Other important possibilities include toxic ingestion, sepsis, and other conditions that raise unmeasured acids in the blood.
Can metabolic acidosis occur with a normal anion gap?
Yes, it can. A child can have normal anion gap metabolic acidosis when bicarbonate is lost or acid handling is impaired without accumulation of unmeasured anions. Common examples include diarrhea and renal tubular acidosis, both of which can cause bicarbonate loss and true metabolic acidosis despite a normal gap.